

Women's & Pelvic Health
Pregnancy Back & Pelvic Girdle Pain
What physiotherapy assessment for pregnancy back & pelvic girdle pain involves, and how care is decided.
This page is patient education — it is not a diagnosis, and it does not replace being assessed.

Common symptoms and signs
Back and pelvic girdle pain in pregnancy is common. Common does not mean it has to be endured without help.
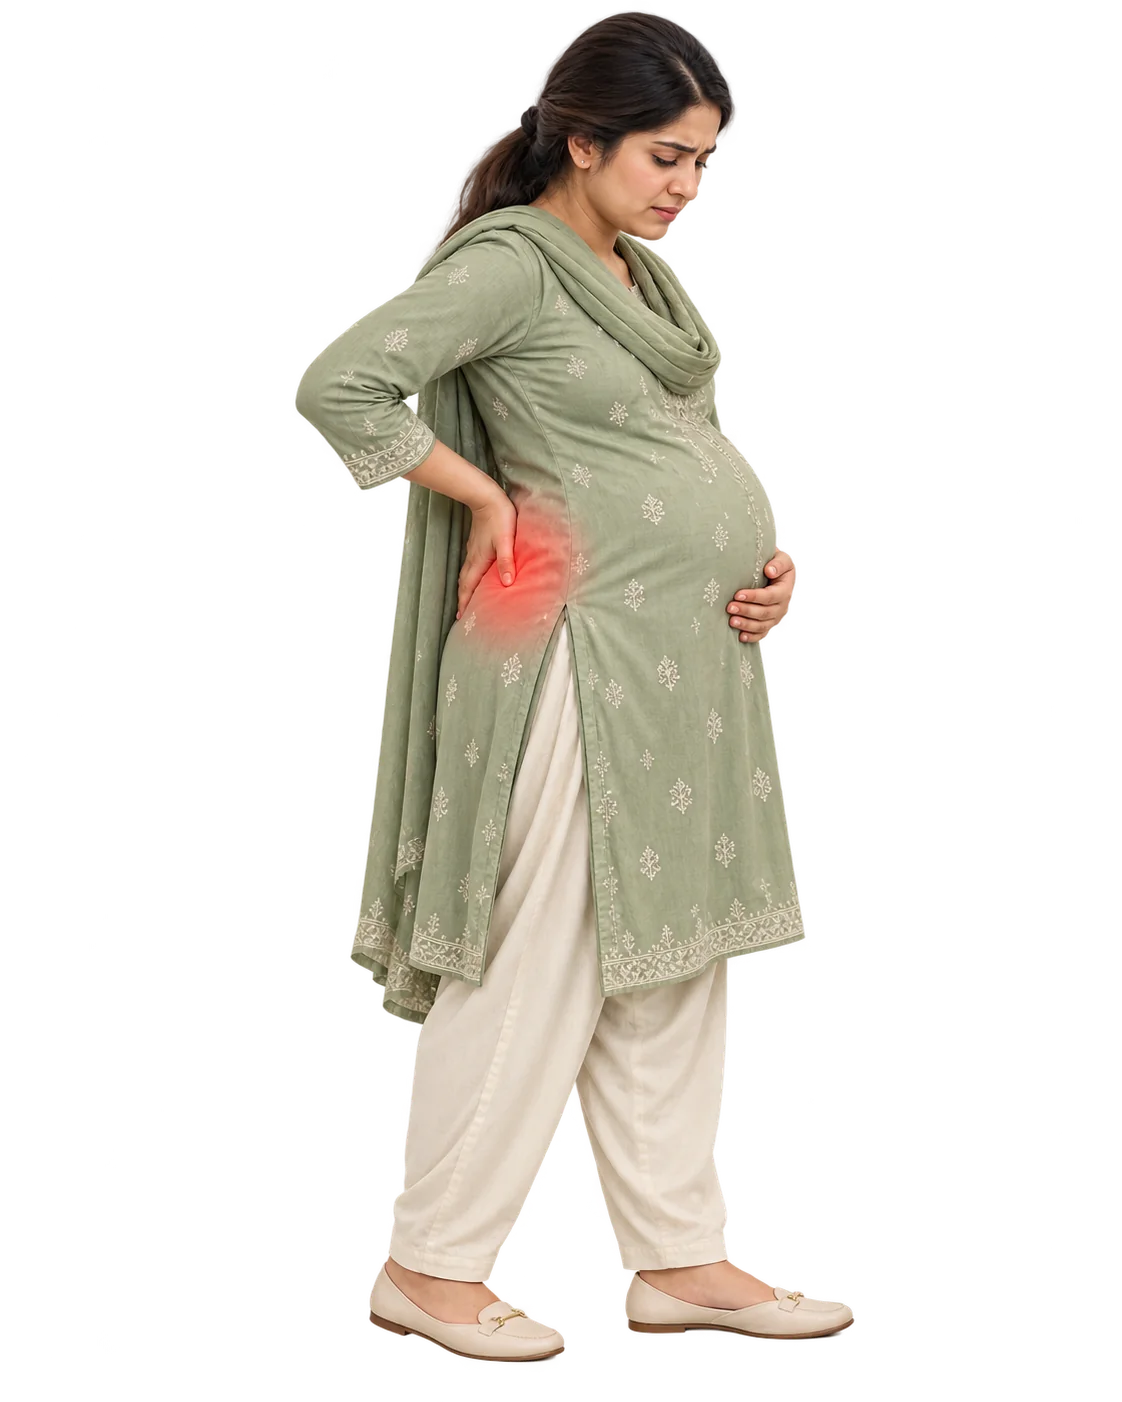
- Pain at the front of the pelvis, the lower back, or one or both sides
- Difficulty turning in bed, climbing stairs or getting out of a car
- Pain when standing on one leg to dress
- A clicking or grinding sensation in the pelvis



These are the things people commonly describe. They are not a checklist for diagnosing yourself — the same symptoms can come from more than one problem, which is what an assessment is for.
Possible causes and contributing factors
Factors commonly associated with this problem. Association is not the same as cause — the same problem has different contributors in different people, and finding yours is part of what assessment does.
- Changes in load and posture as pregnancy progresses
- Hormonal changes affecting the pelvic joints
- Asymmetrical activities and positions
- A previous episode in an earlier pregnancy
When to seek help
When to consider physiotherapy
- Symptoms have persisted beyond the early weeks after birth
- You are avoiding exercise, lifting or intimacy because of symptoms
- You have been told these symptoms are normal and simply to be lived with
- You want to return to running or the gym and are unsure whether it is safe
You do not need to be certain this is you. If you are unsure, describe it to the practice and you will be told plainly whether physiotherapy is the right next step.

How physiotherapy assesses this problem
The same assessment-led approach applies whatever the problem turns out to be. Nothing is treated before it has been assessed.
Step 1: History and symptom pattern
What the symptoms are, when they happen, and how they are affecting daily life. Often the most useful part of the appointment.
Step 2: Assessment at a pace you set
Any physical assessment is explained beforehand, requires your consent, and can be declined or deferred without ending the appointment.
Step 3: Pelvic floor and abdominal wall function
Looking at coordination, strength and the ability to relax — the pelvic floor is not always weak, and assuming it is can make some symptoms worse.
Step 4: Activity and pressure management
What you currently do, and which activities provoke symptoms.




Treatment approach
What care works on, rather than what it promises. What is appropriate for you is decided at the assessment, not from a website.
Working on coordination, strength or relaxation, depending on what the assessment actually finds.
How pressure is managed through the trunk during lifting, coughing and exercise.
Practical strategies for bladder, bowel or pressure symptoms and for the activities that currently provoke them.
Lifting, exercise and running reintroduced in stages, with what to watch for as you progress.



Treatments that may be used
These are techniques a physiotherapist may use. Listing one here is not a recommendation, and none of them is decided before you have been assessed.
 Clinical Pilates
Guided, progressive exercise adapted to a clinical problem — prescribed by a physiotherapist, not run as a general fitness class.
Care & services
Where this problem is looked after, and the programmes it can lead into. The same practice and the same records, wherever the care happens.
 Women's / Pelvic Health
The area of physiotherapy this problem sits within.
 At the clinic
Johar Town, Lahore
 Home physiotherapy
Treatment at your home in Lahore
 Online physiotherapy
Guided sessions remotely
Relevant rehabilitation programmes
- Prenatal Physiotherapy & Exercise
Staying active and comfortable through pregnancy
Who would treat this?
You do not choose a physiotherapist. Describe the problem, and the practice assigns the one whose clinical focus fits it — then reviews that as the picture becomes clearer.
Patient experience
What other patients say
Consented patient story pending
Layout preview · Video not yet availableConsented patient story pending
Layout preview · Video not yet availableConsented patient story pending
Layout preview · Video not yet availableCommon questions
About this problem and assessment — draft copy for clinical review, not personal medical advice.
Do I need an internal examination?
Not always, and never without explanation and consent. Many symptoms can be started with history and external assessment; internal assessment is offered when it would change the plan and you agree to it.
Is leaking after childbirth something I have to live with?
It is common but not something you must accept without help. Assessment looks at pelvic floor coordination, load and habits — weakness is one possibility, overactivity or poor timing is another.
Is pelvic belt use safe in pregnancy?
Support belts may help selected women for short periods when fitted and advised appropriately. They supplement — not replace — strength and movement work tailored to pregnancy stage.
Booking this practice
How do I book an appointment?
Message the practice on WhatsApp with a short description of your problem. The coordinator will reply during clinic hours to arrange a time.
Can I choose which physiotherapist I see?
Booking is with the practice rather than an individual. After you describe the problem, the practice assigns the physiotherapist whose clinical focus fits it. You can read about the team on the physiotherapists page.
Questions about your own case
How long recovery takes, whether you need a scan, and what is safe to do in the meantime all depend on your assessment. Those are worth asking a physiotherapist rather than a website — describe your situation and you will get an answer about you.

Need help with pregnancy back & pelvic girdle pain?
Describe it on WhatsApp. You do not need a diagnosis to get assessed.